

 By
The National Department of Health has issued an urgent nationwide appeal for heightened public awareness and vigilance following a sharp acceleration in laboratory-confirmed mpox cases over recent weeks.

Health authorities report that the country has documented 18 confirmed cases alongside one probable case as of 17 September 2026, signalling a pressing need for collective cooperation to curb further transmission.
Geographic Spread and Demographic Trends
Data released by the department highlights a distinct geographic concentration of the current outbreak. Out of the total confirmed cases, 15 have been localized in the Western Cape—predominantly within the City of Cape Town. Meanwhile, Gauteng has registered 3 cases, and KwaZulu-Natal accounts for 1.
Of primary concern to epidemiologists is the velocity of the recent spread. A striking 13 of the 19 total cases were recorded within a tight window between 13 August and 17 September, pointing toward accelerated local transmission. Demographically, the active cases span individuals aged 23 to 50 years, with a median age of 36.5 years. The demographic profile currently skews heavily male, with 18 males and 1 female affected.
Adding an international dimension to the outbreak tracking, one recent case involves an individual who travelled to Spain earlier in the month and returned to South Africa on 14 September. Having undergone testing abroad after receiving notice of a probable case status, local health officials are actively coordinating with their Spanish counterparts to review and confirm the laboratory test results.
Recognizing Symptoms and Transmission Pathways
Public health officials emphasize that mpox can affect anyone, regardless of race, gender, sexual orientation, or socioeconomic status. Transmission occurs primarily through close physical contact with an infected person. This includes direct skin-to-skin contact with infectious rashes or lesions, as well as handling contaminated materials such as bedding, clothing, or towels.
Furthermore, the virus can spread via respiratory droplets during prolonged face-to-face interactions or uncovered coughing and sneezing.
The incubation period typically ranges from 6 to 13 days post-exposure, though it can extend anywhere from 5 to 21 days. Clinical presentations to watch for include:
- Early systemic signs: Fever, intense headaches, muscle aches, back pain, and profound fatigue.
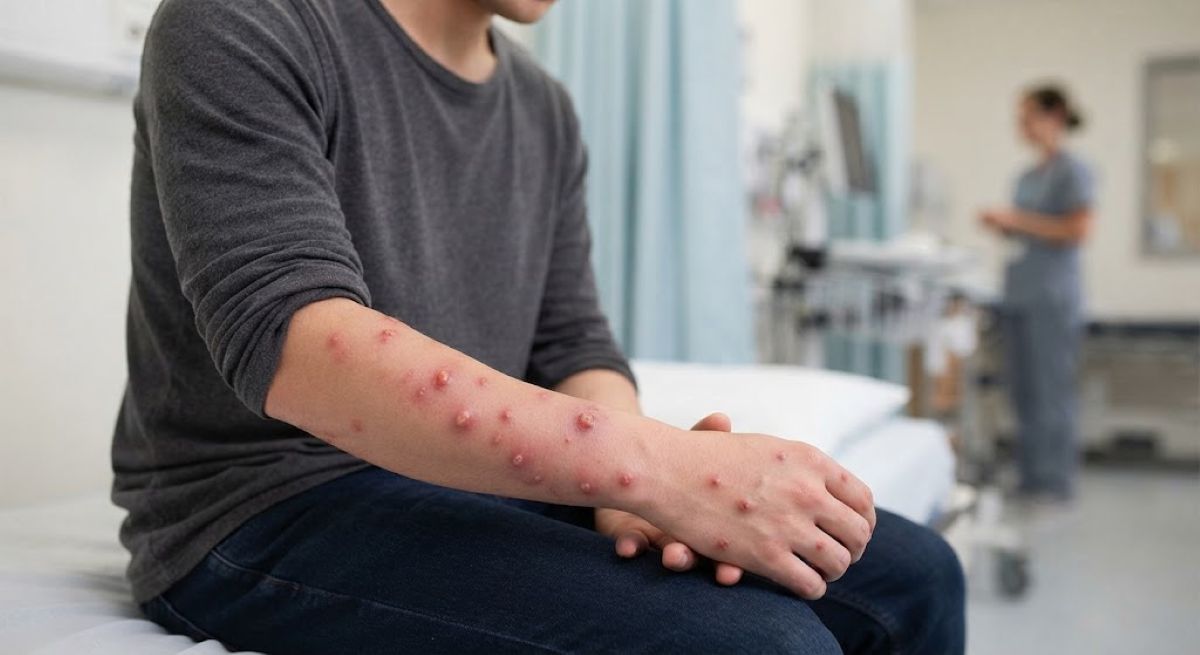
- Dermatological manifestations: Rashes or skin lesions appearing on the face, hands, feet, genitals, or other body parts. These lesions characteristically evolve from flat red spots into bumps, progress to fluid-filled blisters, transition into pus-filled bumps, and finally crust over into scabs.
Anyone displaying these symptoms—especially individuals who have had close contact with a confirmed or suspected case—is urged to seek immediate medical attention and isolate from others to prevent wider exposure.
National Response and Countermeasures
In response to the growing caseload, the government—bolstered by support from the World Health Organization—has secured limited supplies of the MVA-BN mpox vaccine and the antiviral treatment Tecovirimat.
Health authorities are formulating targeted deployment strategies to utilize these medical countermeasures effectively in disrupting community transmission chains. Officials stress, however, that vaccination must be coupled with rigorous adherence to baseline preventive measures, including regular hand hygiene through washing or the use of alcohol-based sanitizers.
Beyond clinical interventions, the Department of Health has issued a strong caution against social stigmatization. Stigma and discrimination can severely undermine public health responses by driving infected individuals away from seeking necessary medical evaluation and care. Communities are instead encouraged to extend support and solidarity to those diagnosed or suspected of carrying the virus.



